
An obstetrician, a birth certificate, and the extraordinary philosophical journey of a perfectly ordinary biological fact.
There are expressions that describe reality, and expressions that arrive carrying an entire philosophical system in their handbag. The latter are particularly fashionable in contemporary academic discourse, where an ordinary fact can scarcely enter a sentence without being accompanied by its social construction, its historical contingency, its political implications and, whenever possible, a reference to Judith Butler.
Consider the expression sex assigned at birth. It sounds terribly sophisticated, doesn’t it? Clinical, compassionate, contemporary. The sort of expression one might expect to hear from a university lecturer who has spent the better part of a decade explaining why everybody else’s vocabulary requires correction. It has the additional advantage of sounding sufficiently technical to discourage ordinary people from asking the rather obvious question: what, precisely, was assigned?
A child is born. The child has a sex. That biological reality precedes the delivery, the obstetrician, the paperwork, the administrative registration, and whatever philosophical crisis the attending physician may allegedly have provoked by looking between the child’s legs. The sex does not materialise because somebody has written an M or an F on a form. Nor does it vanish when the form is misplaced, amended, challenged or ceremonially burned by a postgraduate seminar in gender studies.
And yet we are increasingly encouraged to speak as though something rather more dramatic has occurred. The child has been assigned a sex. Assigned. By whom, precisely? Was there a meeting? A committee? A consultation with the Ministry of Biological Affairs? Did the obstetrician toss a coin, consult the stars, or summon the Sorting Hat from Hogwarts?
One imagines the poor creature emerging into the world, still covered in vernix, while a distinguished gentleman in a pointed hat solemnly deliberates: Slytherin? Ravenclaw? Hmmm… FEMALE! Splendid. Another administrative triumph. Somebody fetch the birth certificate.
The joke is ridiculous because the underlying conceptual manoeuvre is ridiculous. A biological characteristic has been linguistically transformed into the object of somebody else’s decision. Where there was a body, we are invited to contemplate an authority. Where there was a fact to be identified, we are presented with an act of designation. And where there is an assignment, there is an assigner, a procedure, a question of legitimacy and, most conveniently of all, the possibility that somebody has made a dreadful mistake.
The vocabulary does considerable philosophical work before the argument has even begun. And the most entertaining part is that its history can be reconstructed.
I. A Brief Genealogy of an Extremely Convenient Expression
The expression did not descend from heaven, nor was it invented by Judith Butler over breakfast while attempting to deconstruct a boiled egg. Its history is considerably more interesting, and rather less flattering to those who pretend that it is merely a harmless improvement in medical vocabulary.
In November 2022, legal scholar Jessica A. Clarke published a substantial article in the Columbia Law Review, volume 122, pages 1821–1898, titled Sex Assigned at Birth. The article traces the origins of the expression, examines its development within medicine, scholarship and legal advocacy, and argues for its usefulness in disputes concerning transgender rights. It is an especially valuable source for the present discussion because Clarke is an advocate of the terminology. She is explaining its theoretical usefulness from within the intellectual tradition that promotes it.
In 1955, John Money, Joan G. Hampson and John L. Hampson published Hermaphroditism: Recommendations Concerning Assignment of Sex, Change of Sex, and Psychologic Management in the Bulletin of the Johns Hopkins Hospital. Their work concerned children with atypical sexual development, particularly circumstances in which genital anatomy presented difficulties for classification and subsequent management. The authors proposed that decisions about sex of rearing should consider external genital appearance, the possibilities of surgical reconstruction and potential hormonal interventions.
Here, the language of assignment had a recognisable clinical purpose. Physicians were addressing unusual cases in which medical and social decisions were being made amid uncertainty about anatomy, future development and treatment. Their framework reflected assumptions characteristic of mid-twentieth-century medicine, including extraordinary confidence in the ability of surgery and upbringing to establish a stable psychosexual outcome. Those assumptions were subsequently challenged, and rightly so. The historical context, however, is essential: this was a specialised vocabulary associated with exceptional medical circumstances, not a general proposition that every newborn’s biological sex depended upon a physician’s discretionary selection.
By 1960, Edgar Burns, Albert Segaloff and G. M. Carerra were using the expression assignment of sex at birth in an article published in The Journal of Urology. During the following decades, related terminology became familiar in medical and psychiatric discussions of transsexualism, sex reassignment and the distinction between bodily characteristics and psychological identity. The earlier medical history was hardly a festival of postmodern emancipation. Some of the practices from which this vocabulary emerged involved intensive intervention upon children whose capacity to participate in such decisions was necessarily limited.
The next stage occurred within transgender scholarship and activism. During the 1990s, the language of assignment was increasingly adopted to describe the relationship between an individual’s original sex classification, subsequent identity and right to self-definition. Leslie Feinberg’s Transgender Warriors (1996) employed the expression sex they were assigned at birth. Susan Stryker’s work likewise contributed to a vocabulary in which identities and social expectations could be understood in relation to categories established earlier in life.
The change was conceptually significant. A term associated with unusual medical decisions had acquired a general explanatory function. It could now be applied to people whose biological development had never presented a diagnostic difficulty whatsoever. An exceptional clinical concept had escaped the clinic and entered the expanding vocabulary of identity. And from there, it entered the law.
In 2002, New York City and Philadelphia incorporated references to sex assigned at birth into their antidiscrimination provisions. California adopted related language in 2004. During the 2010s, the terminology became increasingly visible in American litigation, and it appeared in federal healthcare regulatory language in 2016. Clarke’s examination of the Westlaw database reported a sharp increase in relevant decisions after 2014. These are findings about a particular legal search, not a measurement of everyday speech, but the direction of travel is unmistakable: the expression had become part of legal argument.
Then came the acronyms. AFAB, for assigned female at birth, and AMAB, for assigned male at birth. Apparently ordinary English had become insufficiently bureaucratic, and the discussion required something resembling the registration codes of an international airport. The acronyms were hardly meaningless flourishes: they offered an alternative to older transition labels and expressed theoretical choices concerning the relationship between sex, gender and identity.
This is where the archaeology becomes particularly useful. Clarke writes in the abstract of her article:
“Sex assigned at birth is intended to displace the concept of ‘biological sex.’”
There it is. Not a misunderstanding invented by a disgruntled conservative journalist. Not a hallucination produced by an intoxicated homosexual writing from Montevideo. An explicit statement in a major academic law review, made by a scholar defending the expression and its conceptual usefulness. Clarke argues that the concept of biological sex is more complicated than conventional classifications suggest, and that assignment terminology helps reveal institutional and normative dimensions of sex categorisation. She regards that shift as useful for arguments concerning autonomy, equality, privacy and transgender rights.
That is her argument. And I am equally entitled to consider it complete rubbish, utter nonsense, and one of the most preposterous conceptual manoeuvres ever smuggled into public discourse under the respectable appearance of academic terminology. A contested theory does not become a biological discovery merely because its preferred vocabulary acquires a citation index and a place in institutional guidance. If the substitution is explicitly defended for its theoretical consequences, we are perfectly entitled to discuss those consequences rather than pretend that the two expressions are interchangeable.
II. The Obstetrician Who Must Not Be Named
He who controls the terms often controls the horizon of the debate. He Who Must Not Be Named. Oh, I’m terribly sorry. He who controls the terms. One can hardly be blamed for confusing the two. In the more melodramatic versions of this narrative, the obstetrician appears to have been cast as Lord Voldemort, lurking beside the delivery table in surgical scrubs, ready to impose a sexual destiny upon an unsuspecting infant. A flick of the wand, a solemn pronouncement, a bureaucratic designation, and an entire life supposedly transformed by the tyranny of medical authority.
Sexus Assignatus! How terribly sinister. One wonders whether the Ministry of Magic has a Department of Obstetrics.
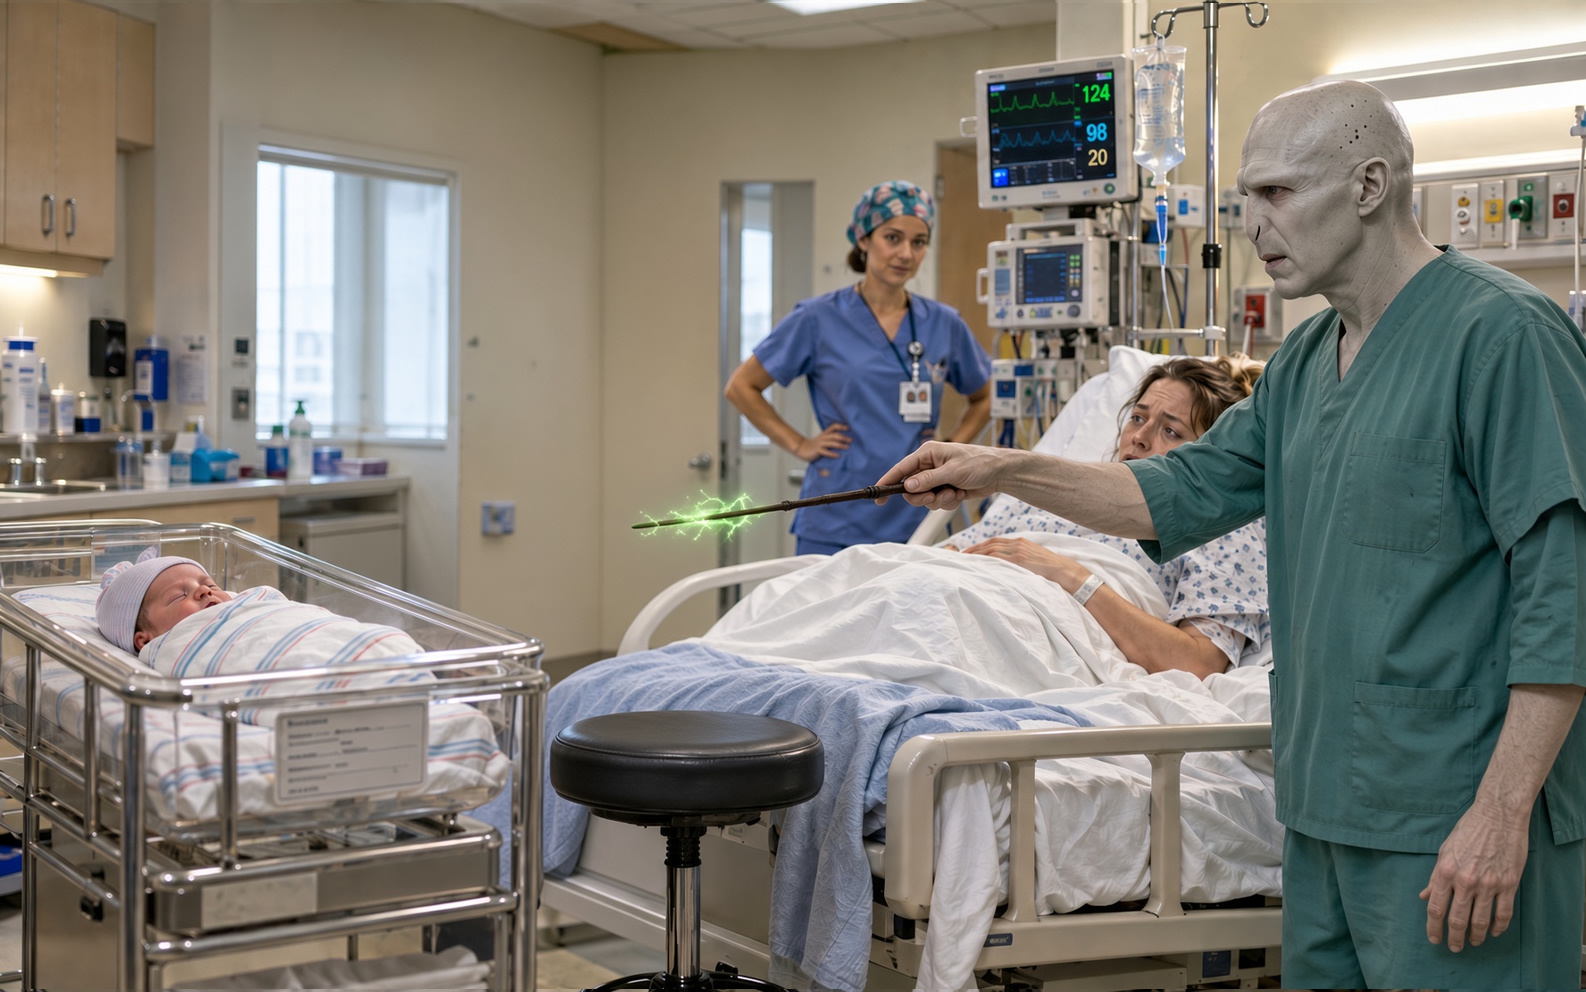
Unfortunately for this delightful fantasy, sexual development begins long before any obstetrician enters the scene. Chromosomal constitution, gonadal differentiation, hormonal pathways and the development of reproductive anatomy belong to processes occurring during embryonic and fetal life. They are not summoned into existence by a physician’s declaration. In an ordinary delivery, the clinician identifies anatomical characteristics that are already present and the corresponding information is documented. A baby does not acquire testes because somebody writes male, and a female reproductive developmental pathway does not begin operating because a registrar selects a box.
An administrative act can establish what a document says. It does not manufacture the biological condition to which the document refers. An error on a birth certificate remains an error on a birth certificate. Correcting the document may alter somebody’s legal status or administrative records, but cannot retroactively reconstruct their embryological development. The statement and the state of affairs to which it refers are not the same thing.
At this point the existence of differences of sex development is frequently invoked, as though an exceptional clinical difficulty settled the ontological status of every ordinary birth. Very well. Let us discuss those cases properly rather than treating them as a magical incantation intended to dissolve the distinction.
III. The Exceptional Case Is Not a Licence to Rewrite the Ordinary One
There are infants born with atypical genital anatomy or differences involving chromosomal, gonadal, hormonal and anatomical development. In some cases external appearance does not provide sufficient information to establish the underlying condition or determine appropriate clinical management. And what does contemporary medicine do in those circumstances? It investigates. It does not summon a philosophical committee to flip a coin over the incubator. It does not invite the obstetrician to indulge in metaphysical creativity between delivering the placenta and completing the discharge paperwork.
Modern evaluation may involve karyotyping, molecular genetic studies, hormonal and biochemical investigations, pelvic or abdominal imaging, assessment of gonadal anatomy, and consultation with paediatric endocrinologists, geneticists, urologists and other specialists. The investigations depend on the clinical presentation; some results or developmental considerations require reassessment over time. The purpose is to understand the patient’s actual biological condition and the implications of any clinical or administrative decision. Even when uncertainty persists, the physician’s discretion is constrained by evidence, ethical duties and the patient’s prospective interests.
The international consensus statement of 2006 recommended that gender assignment in newborns with differences of sex development should not precede expert evaluation, and emphasised multidisciplinary management and communication with families. Later British endocrine guidance developed diagnostic pathways incorporating chromosomal, hormonal, anatomical and genetic investigations. Here is the magnificent irony: in the circumstances where a decision about sex of rearing or legal classification may genuinely be necessary, recommended modern practice is to avoid making that decision precipitously in the delivery room.
The medically complex newborn is evaluated. The findings are examined. The family is informed. Specialists consider the condition, its developmental implications and the available evidence. Sometimes clarification comes quickly; sometimes uncertainty remains despite extensive investigation. In either event the decision, when one must be made, emerges from a process rather than from the obstetrician’s sovereign declaration. Nor is the process always complete at birth: the developing patient, future autonomy and long-term consequences can matter decisively.
Thus the ordinary case involves no meaningful discretionary choice about the underlying anatomy, while the exceptional case may require delayed specialist assessment of a difficult classification. Neither situation supports the fantasy that the child’s biological characteristics are created by an act of assignment. Quite the opposite: the examination is undertaken because those characteristics exist independently of the decision and must be understood before anyone acts.

It is 2026. We have molecular diagnostics, endocrine investigations, specialist imaging and multidisciplinary clinical teams. There is remarkably little excuse for describing ordinary identification of a newborn’s sex as if obstetrics were still governed by a physician’s unexamined personal preferences from the 1950s. And even less excuse for presenting that caricature as an advanced criticism of medical authority.
IV. The Philosophical Trick Hidden in the Grammar
Consider the difference between two expressions: sex at birth and sex assigned at birth. The first refers directly to a biological characteristic at a particular moment in a person’s life. The second introduces an agent and an act. Someone has assigned something to somebody else. The proposition now invites questions concerning the assigner’s authority, the legitimacy of the procedure, the correctness of the judgment and the possibility that the classification should subsequently be challenged.
The shift is subtle enough to pass unnoticed in ordinary conversation yet substantial enough to reorganise a debate. Instead of beginning with the body, we begin with the authority that supposedly designated it. Instead of asking what the organism is, we are encouraged to ask who decided what the organism would be called. The conceptual emphasis has migrated from biological development to institutional power, and with it comes the possibility of transforming an error of classification into an error of ontology.
If the original sex was assigned, perhaps the assignment was mistaken. If it was mistaken, perhaps a later self-description corrects the earlier error. And if that self-description is treated as the authoritative truth, the original biological description can gradually be displaced from the argument altogether. This progression is rhetorically elegant. Its logical foundations are less impressive. An incorrect classification presupposes something against which its correctness can be assessed. A label can fail to describe a biological condition without thereby creating that condition.
The subsequent adoption of a different identity does not, merely by occurring, demonstrate that the person’s original biological sex was incorrectly recognised. The difference between an experience and its interpretation matters here. Someone may experience profound bodily estrangement, distress concerning sexual anatomy or an enduring identification with the opposite sex. Those experiences deserve serious phenomenological and clinical attention. Their existence does not independently establish that the person’s original sex was an externally imposed fiction.
That additional argument is precisely what the terminology risks concealing. A rhetorical construction that begins by shifting attention to the classifier can finish by treating the classificatory act as the source of the underlying reality. Biology is progressively relocated into language, while the language acquires an authority over physiology that no grammatical operation can justify. We have discovered that human beings describe the world through concepts and are now behaving as though the world itself had been waiting impatiently for somebody to invent a vocabulary.
The temptation becomes especially seductive when moral commitments enter the discussion. If a description is associated with a politically disfavoured conclusion, revising the description can appear to offer a shortcut around the disagreement. Unfortunately, changing the vocabulary does not resolve the empirical or ontological question. It merely changes the terms in which the question is asked.
V. Judith Butler, or the Extraordinary Art of Making a Simple Question Last an Entire Afternoon
It would be terribly satisfying to attribute the invention of this expression directly to Judith Butler. Unfortunately, the historical evidence refuses to cooperate. Assignment terminology predates her most influential work and emerged from medical contexts quite unlike the contemporary theoretical landscape. A dreadful disappointment. I was rather looking forward to blaming her personally.
Nevertheless, Butler’s philosophical work makes an illuminating comparison, particularly concerning bodily materiality, social norms and the processes by which categories become intelligible. In Gender Trouble and Bodies That Matter, Butler investigates how categories of sex and gender are constituted, regulated and reproduced through social practices. Her account is more sophisticated than the internet slogan that anybody can become anything simply by declaring it. But sophistication does not confer immunity from criticism.
The relevant question is whether analysis of norms governing sexual classification demonstrates that the underlying biological distinctions depend upon those norms for their existence. Social expectations about what males and females ought to do vary historically. Administrative categories may be revised. Institutions distribute rights and duties in changing ways. None of these observations establishes that the developmental processes producing sexually differentiated organisms are themselves biologically constituted by social recognition.
The distinction between the meaning attributed to a body and the developmental reality of that body cannot simply be dissolved in an account of discourse. The fact that a body is always encountered within a human world of concepts does not make its physiology dependent upon those concepts. One can interrogate a category indefinitely; eventually one must explain what the category describes, what claim is being made about its referent, and what evidence distinguishes a successful description from an unsuccessful one.
I admit to an unusual relationship with Butler’s intellectual legacy. I admire her philosophical ambition, her willingness to challenge inherited categories and the extraordinary influence of her work. I despise the tendency, particularly among some intellectual descendants, to treat conceptual complexity as though it were itself an answer. Otherwise the discussion becomes an elegant procession of qualifications, each one more exquisitely formulated than the last, while the original question sits quietly in the corner, ageing.
It is possible to recognise the philosophical importance of language without elevating language into an omnipotent creator of biological reality. It is also possible to examine the political history of classifications without supposing that the historical contingency of their social interpretation renders their natural referents equally contingent. Somebody ought eventually to define the bloody terms before the éclairs run out.
VI. The Bureaucratic Metaphysics of AFAB and AMAB
There is a special sort of intellectual comedy in watching an expression expand until it becomes a compulsory component of ordinary speech. First comes sex assigned at birth, presented as a refinement upon older terminology. Then assigned female at birth and assigned male at birth. Then AFAB and AMAB, whose appearance of technical precision can obscure the conceptual choices from which they emerged. The result is vocabulary that sounds increasingly medical while performing increasingly extensive theoretical work.
A person who was born female is described as AFAB; a person who was born male as AMAB. The biological characteristic has been displaced by a reference to an act performed upon the individual at birth. Even where the original identification presented no diagnostic uncertainty, the grammar retains the framing of an assignment. Terms migrate into journalism, academic writing, institutional guidance and everyday conversations in which male or female would communicate the relevant biological information perfectly well.
Eventually the vocabulary becomes a marker of intellectual affiliation. Those who decline to employ it are expected to justify themselves, while those who insist upon it are permitted to behave as though the philosophical dispute had already been settled. A marvellously efficient arrangement, provided one happens to agree with the people who selected the words.
The alternative requires very little effort: sex at birth, or simply birth sex. Three words in one case, two in the other. English survives. Medicine continues operating. Obstetricians are relieved of their imaginary metaphysical powers. And the newborn may possess biological characteristics without awaiting an administrative verdict.
If the discussion concerns a birth certificate, describe what that certificate records. If it concerns a complex clinical decision, set out the findings and explain the decision. If it concerns someone’s gender identity, discuss that experience on its own terms. There is no intellectual necessity to force every subject through the same terminological apparatus. Simplicity need not deny genuine complexity; it can simply decline to manufacture complexity where none is required.
VII. The Sorting Hat May Finally Return to Hogwarts
We have reached a peculiar moment in public discourse. A biological characteristic that ordinary language has described for centuries now arrives accompanied by a bureaucratic verb, two fashionable acronyms and an elaborate theoretical history. A physician who identifies a newborn’s sex is rhetorically recast as an authority assigning an identity. A specialised vocabulary becomes generalised, and the resulting formulation is presented as neutral progress.
Clarke’s historical work supplies a sound reason to dispute that supposed neutrality. It documents the medical origins of assignment terminology, its adoption in transgender scholarship and advocacy, its expansion into law, and the theoretical purposes attached to replacing references to biological sex. Clarke offers a defence of that development. My conclusion is rather different: a biological fact does not become an administrative invention merely because somebody chooses to describe it through the language of administration.
Biological development precedes its recognition. No philosophical framework acquires authority over that development by changing the grammatical subject of a sentence. Medicine, law, identity and social policy may ask different questions, and their classifications can serve different purposes; confusing those purposes produces errors that will not be corrected by insisting upon a preferred vocabulary.
A contested framework should be defended by argument, not quietly installed through terminology. And the freedom to question an argument necessarily includes the freedom to question the words in which it is framed. So I propose a modest linguistic rebellion: no AFAB, no AMAB as compulsory replacements for ordinary biological descriptions. No more pretending every newborn underwent discretionary sex designation just because a specialised medical expression became fashionable.
The whole enterprise strikes me as complete nonsense, embellished with a great deal of philosophical embroidery and the occasional spectacular flourish of bureaucratic absurdity. And Judith Butler, whom I admire and despise in approximately equal measure, may take comfort in having escaped responsibility for inventing this particular phrase. The historical record has deprived me of that accusation, which is frankly inconsiderate of it.
I would nevertheless be delighted to debate the philosophical implications with her, preferably over Scotch, cucumber sandwiches and a properly prepared éclair. We might disagree about almost everything, but I should insist on one elementary condition of the evening: that the relevant terms be defined before dessert.
Until then, I shall persist in using an expression so offensively uncomplicated that it may scandalise an entire department of gender studies. Sex at birth. The baby has a sex. The paperwork doesn’t give it one. And the Sorting Hat can finally return to Hogwarts, where arbitrary classification is at least accompanied by a decent education in magic.
References
- Clarke, J. A. (2022). Sex Assigned at Birth. Columbia Law Review, 122(7), 1821–1898.
- Money, J., Hampson, J. G., & Hampson, J. L. (1955). Hermaphroditism: Recommendations concerning assignment of sex, change of sex, and psychologic management. Bulletin of the Johns Hopkins Hospital, 97, 284–300.
- Burns, E., Segaloff, A., & Carerra, G. M. (1960). Reassignment of sex: Report of 3 cases. The Journal of Urology, 84, 126.
- Feinberg, L. (1996). Transgender Warriors: Making History From Joan of Arc to RuPaul. Beacon Press.
- Lee, P. A., et al. (2006). Consensus statement on management of intersex disorders. Archives of Disease in Childhood, 91, 554–563.
- Ahmed, S. F., et al. (2016). Society for Endocrinology UK guidance on the initial evaluation of an infant or an adolescent with a suspected disorder of sex development (revised 2015). Clinical Endocrinology, 84, 771–788.
- Stryker, S. (2008). Transgender History. Seal Press.
- Butler, J. (1990). Gender Trouble: Feminism and the Subversion of Identity. Routledge.
- Butler, J. (1993). Bodies That Matter: On the Discursive Limits of “Sex”. Routledge.


Deja una respuesta